OUR CARE MODEL
Find risk early and treat it where patients live
The signs of an avoidable admission appear at home days before anyone sees them in a clinic. Our care model is designed for those days in between visits and keeps people healthy and stable at home.
The engine behind continuous care
Remote PatientMonitoring Clinically
Governed AI Clinical
Intervention
Powered by daily data from home
- Daily Vitals
- Symptom Surveys
- No Smartphone Needed
- Hundreds of Devices
- Wi-Fi Not Required
- MyCare App
Daily vitals and symptoms from home join claims, pharmacy, and chart data, so each reading is seen in context.
Guided by models that rank risk
- Alert Prioritization
- Candidate Selection
- Disenrollment Prediction
- Outcome-Trained Models
- Deterioration Detection
- Clinical Governance
Models trained on two decades of real-world outcomes flag early decline and rank who needs a clinician first.
Delivered by clinicians who act
- Orders and Referrals
- Primary Care
- Chronic Disease Management
- Prescribing
- Post-Discharge Follow-Up
- ED Diversion
Licensed clinicians prescribe, adjust treatment, and place orders and referrals, then see every case through.
What continuous care delivers
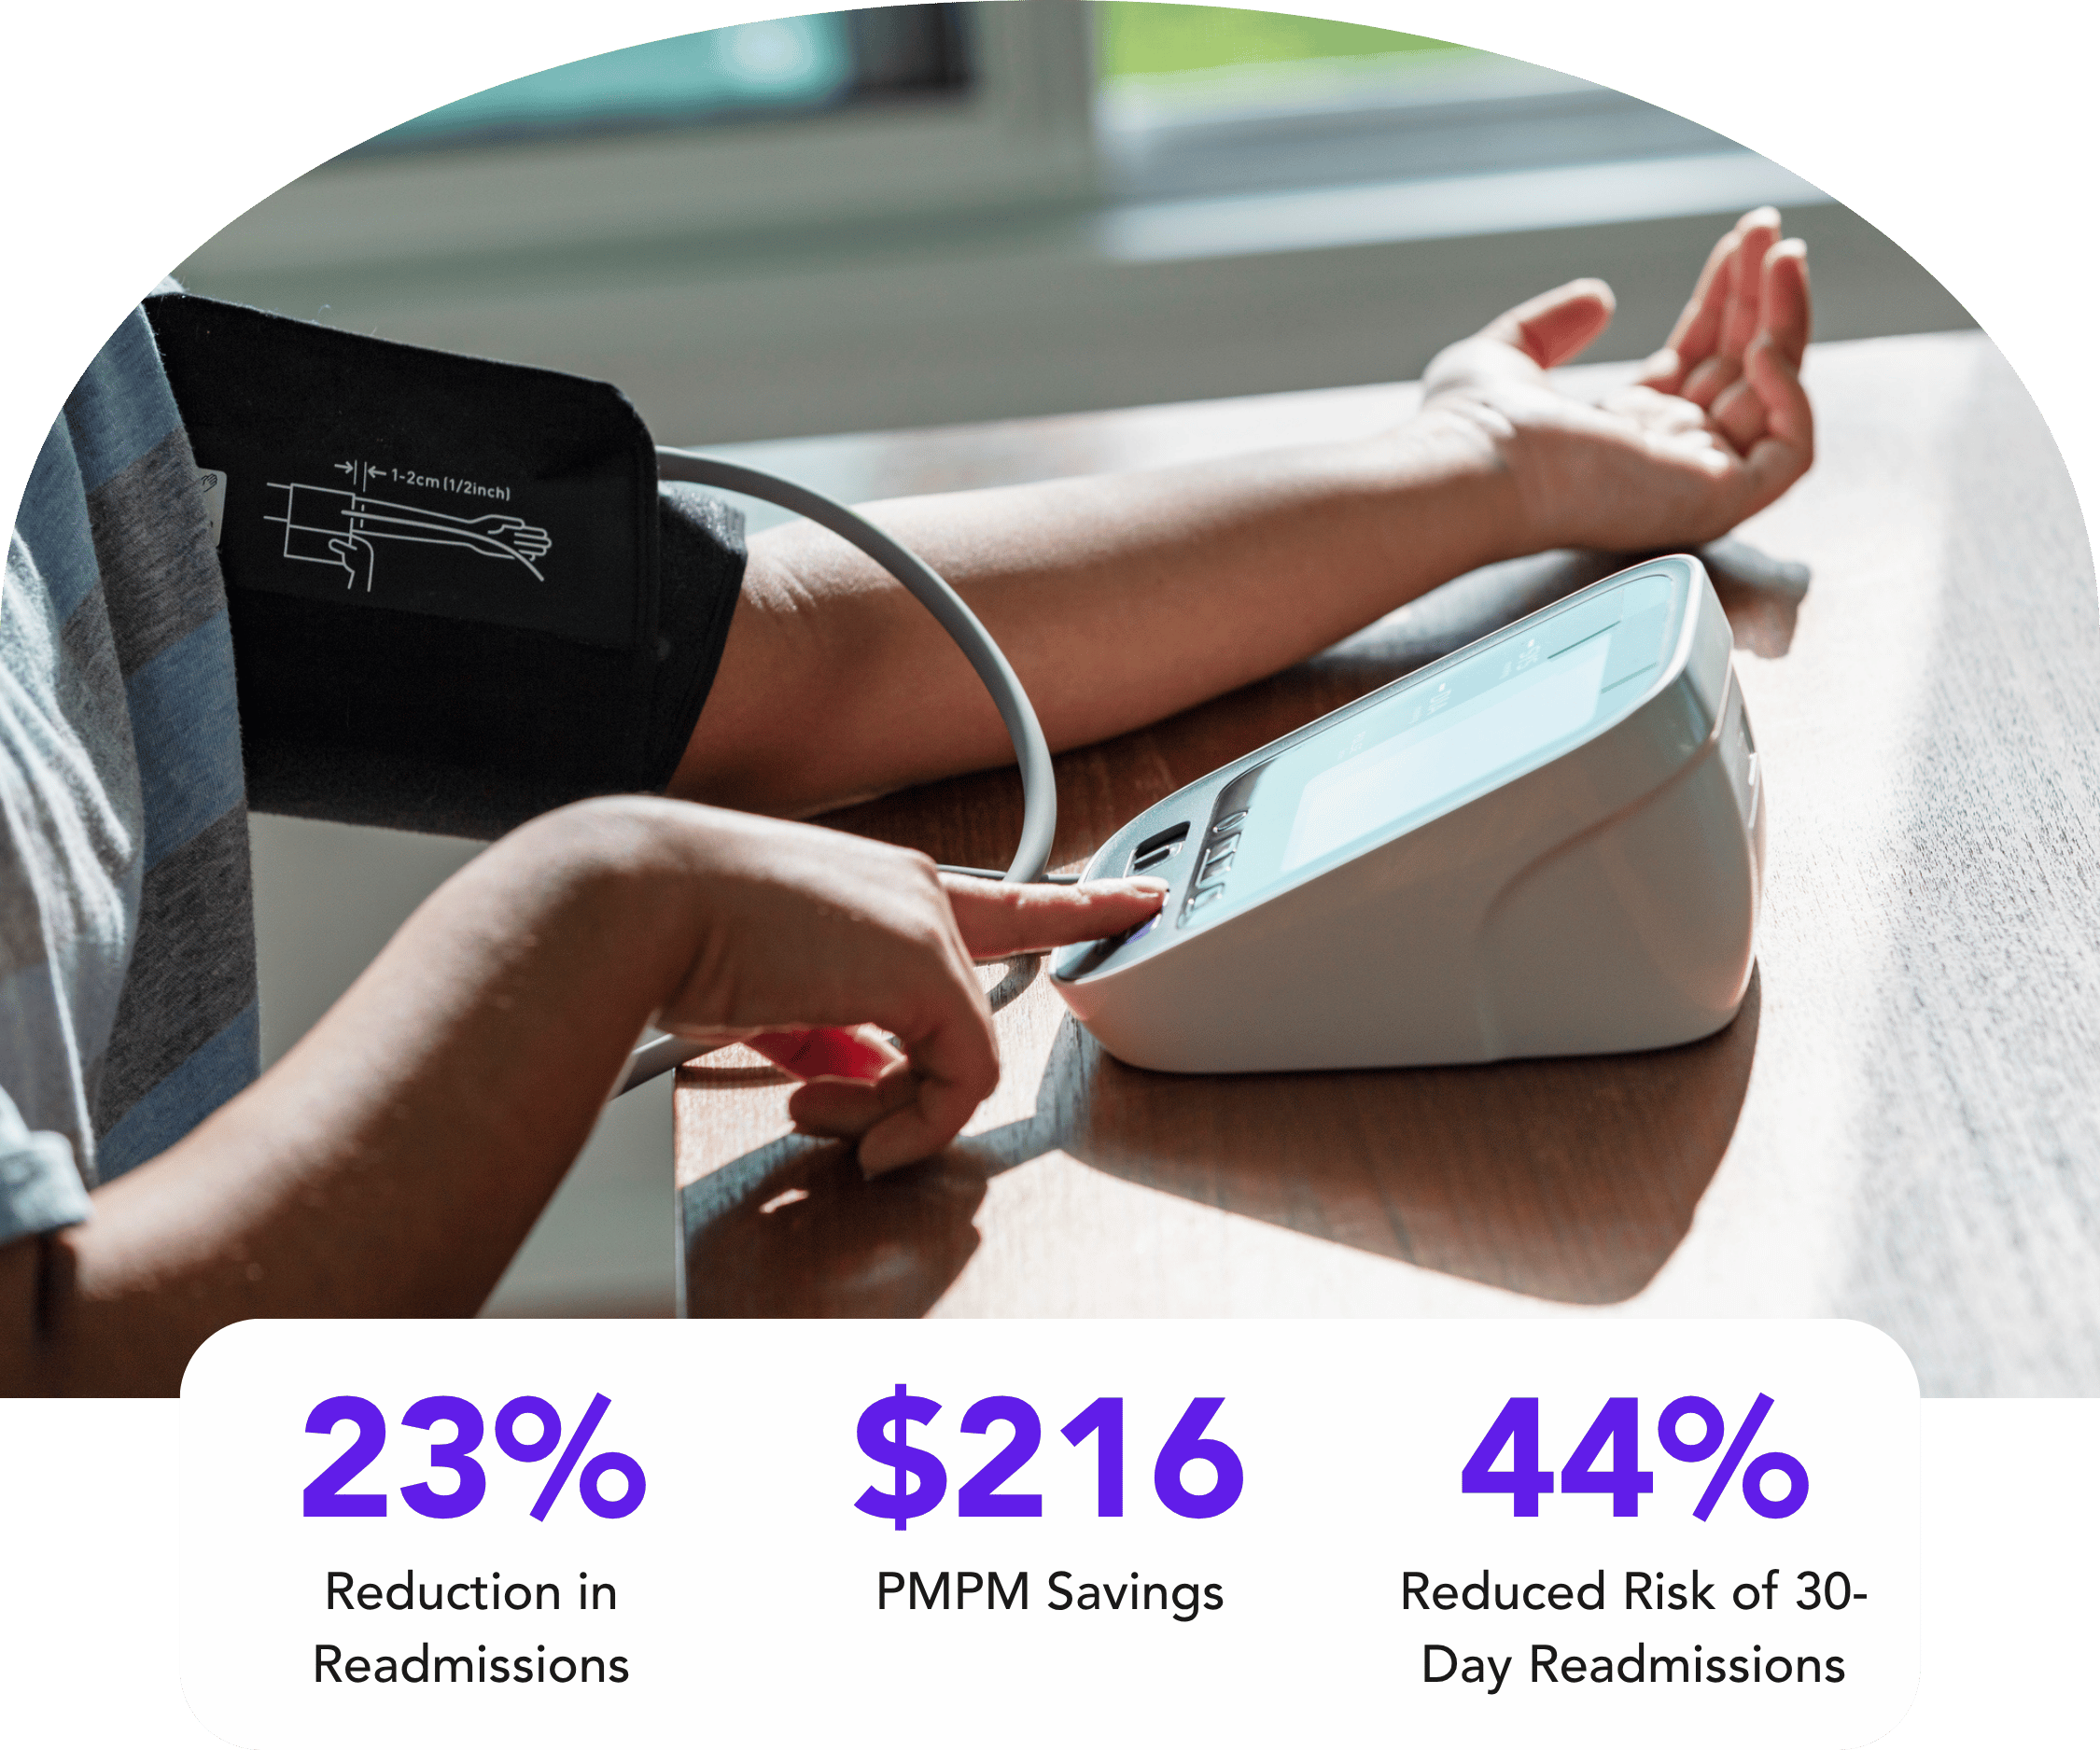
PMPM Savings, Medicaid Heart Failure Study
Lower Odds of 30-Day Readmission After Discharge
Blood Pressure Control Sustained at 18 Months
Patient Satisfaction

Connected however a patient lives
Patients connect by smartphone app, cellular tablet, cellular modem, or phone call, so daily readings don’t depend on home internet or comfort with technology. Our team handles enrollment, shipping, setup, and support.
Clinical judgment always stays with clinicians
Models direct clinical attention, but they never replace clinical judgment. Every decision belongs to a licensed clinician, and our clinical leadership governs every model we use, from validation before launch to monitoring afterward.


Alongside the physicians patients already have
Our clinicians provide continuous primary care for heart failure, diabetes, hypertension, COPD, and other chronic conditions. They extend the care of each patient’s own physician or serve as the primary care provider themselves.
PEER-REVIEWED STUDY
Fewer heart failure admissions, lower cost of care, 3.3x return
Geisinger Health Plan added AMC Health home monitoring to the case management it already ran for Medicare Advantage members with heart failure. Over five years of claims data, enrolled members were admitted less often, readmitted less often, and cost the plan 11% less. Published in Population Health Management.